What Does the Anion Gap?
The anion gap is a lab-derived value that helps clinicians evaluate electrolytes and spot an acid-base abnormality. It is derived from common blood chemistry results, especially sodium, chloride, and bicarbonate. Because it indicates the balance of measured ions in the blood, the anion gap can function as a useful diagnostic clue during metabolic acidosis evaluation.
In simple terms, the anion gap compares the positively charged ions and negatively charged ions reported on an electrolyte panel. Most commonly, the calculation uses serum sodium as the main measured cation, then removes serum chloride and serum bicarbonate. The resulting anion gap result assists in distinguishing between different causes of EG ingestion anion gap acidosis and directs further lab interpretation.
An anion gap calculator simplifies this calculation by applying the standard equation automatically. That is helpful because the value itself is only part of the picture; the real value comes from understanding what the number indicates about electrolyte balance and the likely cause of the patient’s symptoms or test result.
Anion Gap Equation & Input Values
The standard anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Typical calculation tools require 3 inputs: sodium, chloride, and bicarbonate. These values typically are obtained from a basic metabolic panel or similar blood test. When added, the calculator calculates the anion gap and helps support a more informed clinical assessment.
Some methods may include potassium in a different version of the equation, but the most frequently used bedside and online approach relies on sodium, chloride, and bicarbonate. This makes the calculation efficient for rapid blood chemistry review and routine lab interpretation.
To use an anion gap calculator properly, make sure the numbers are from the same sample and expressed in compatible units, typically mEq/L. If the lab reports values in another format, convert them before calculating to avoid an incorrect result.
How to Calculate the Anion Gap Step by Step
To calculate anion gap manually, start out with the three values from the electrolyte test panel. Then follow the formula in order. A precise step-by-step approach reduces errors and improves the accuracy of the test result.
Step 1: Locate the serum sodium value.
Step 2: Identify the serum chloride value.
Step 3: Identify the serum bicarbonate value.
Step 4: Add chloride and bicarbonate together.
Step 5: Subtract that total from sodium.
Here is a simple calculation example:
If the test values are sodium 140 mEq/L, chloride 104 mEq/L, and bicarbonate 24 mEq/L, the calculation is:
140 - (104 + 24) = anion gap in chronic kidney disease 140 - 128 = 12 mEq/L
In this example, the anion gap is 12 mEq/L, which is often within a standard reference range depending on the laboratory. This kind of worked example is useful because it shows how the numbers on a blood test become a useful diagnostic clue.
When using an online calculator, the same steps happen right away. Still, understanding the arithmetic helps you check the output and connect it to the broader picture of electrolyte balance and acid-base disorder.
Normal Anion Gap Range and Reference Values
The normal range for the anion gap depends on the laboratory and the measurement method used. There is no single standard reference range, which is why clinicians read the result in context rather than depending on one fixed cutoff.
Many labs report a normal anion gap in a range that is approximately the low teens, but the exact value can vary with assay differences and laboratory variation. Because of that, it is best to compare the test result with the specific reference interval shown on the blood test report.
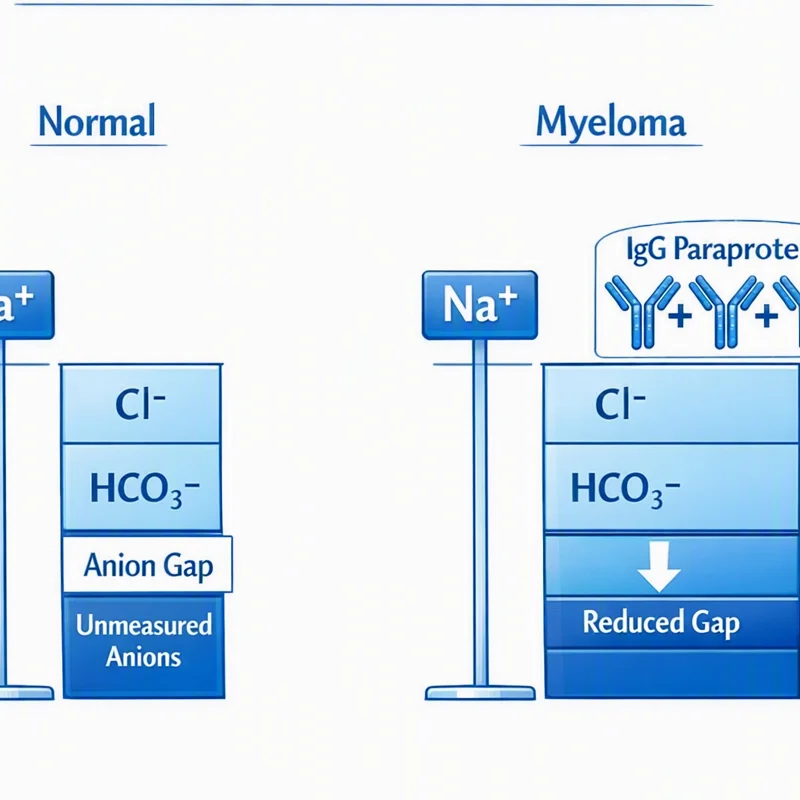
Albumin also matters. Since albumin is an unmeasured anion, low albumin can decrease the apparent gap and make a high-gap problem more likely to be overlooked. That is one reason a result should always be interpreted using both the numeric value and the surrounding clinical context.
If the value sits near the upper end of the normal reference range, it may still call for attention in a patient with symptoms or other lab abnormalities. A borderline test result can give a useful diagnostic clue even when it does not obviously exceed the range.
What a Elevated Anion Gap Can Indicate
A elevated anion gap frequently indicates metabolic acidosis caused by the buildup of uncounted acids in the blood. This result is sometimes called high gap acidosis, and it can be an important warning sign that additional testing is needed.
Typical causes include lactic acidosis, ketoacidosis, and toxic alcohol ingestion. Every one of these conditions shifts the blood chemistry in a different way, but each can increase the anion gap by bringing in acid or acid-like substances that are not directly counted in the standard panel.
Lactate-related acidosis may occur when tissues do not receive enough oxygen or when severe illness disrupts normal metabolism. Ketoacidosis can occur in uncontrolled diabetes, prolonged fasting, or other states of excess fat breakdown. Toxic alcohol ingestion is another serious cause that can create dangerous acid-base changes and requires urgent evaluation.
When the anion gap is elevated, the number alone does not reveal the cause. Instead, it acts as a key clue that prompts a broader review of symptoms, vital signs, medication history, and additional laboratory results. That is why the value is most useful as part of a structured overall assessment.
What a Normal Anion Gap May Indicate
A normal, or nearly normal, result does not rule out an acid-base disorder. In fact, normal anion gap acidosis can still signal a meaningful underlying condition. This pattern is often called non-anion gap metabolic acidosis or non-gap acidosis.
Common causes include diarrhea, renal tubular acidosis, as well as hyperchloremia. In these cases, bicarbonate is depleted, but chloride increases to maintain electrical balance, so the calculated gap may remain in the normal reference range.
Diarrhea can result in bicarbonate depletion from the gastrointestinal tract. Renal tubular acidosis disrupts the kidneys’ ability to handle acid or bicarbonate properly. Hyperchloremia, which means an elevated chloride level, can reflect the body’s compensation for bicarbonate loss or another underlying condition.
As a result, a normal gap should not be read as “everything is fine.” It only suggests a different pattern of acid-base disorder. Careful electrolyte interpretation and review of the broader blood test results are still essential.
Serum albumin Correction and Adjusted Anion Gap
Albumin correction is important because low albumin can make the measured gap appear lower than it truly really is. When low albumin is present, the raw number may downplay the degree of unmeasured anions in the blood. In those cases, a adjusted anion gap can offer a more precise estimate.
Albumin possesses a negative charge and plays a major role to the body’s unmeasured anion pool. If albumin is lowered, the gap may drop even if an acid load is there. This is why many clinicians follow an albumin-adjusted approach, especially when reviewing unexplained acidosis.
The exact correction method can change by institution, but the principle is the same: modify the result based on the albumin level so the adjusted value better matches the patient’s actual acid-base status. This can help prevent a missed diagnosis in someone whose laboratory test shows low protein levels.
Total protein may also clarify the result, although it is not used directly in the standard equation. Together with albumin, it can support a more comprehensive view of the patient’s biochemical state and enhance the quality of lab interpretation.
How to Use the Anion Gap Calculator Safely
An anion gap calculator is a useful resource, but it should be used as part of thoughtful electrolyte interpretation. The number is only reliable when you consider the clinical context, the patient’s complaints, and the remainder of the blood chemistry.
Before using the result, confirm that the inputs come from the identical electrolyte panel and that units are consistent. If the sodium, chloride, or bicarbonate values are old or misaligned, the calculated number may be inaccurate. Good lab interpretation depends on precise, current data.
It is also essential to avoid overinterpreting a one test result. A normal result does not exclude significant illness, and an elevated result does not determine the cause by itself. The calculator is best understood as a assistive tool for medical disclaimer purposes: it can help direct thinking, but it does not replace professional judgment or formal diagnosis.
If the result suggests metabolic acidosis or some other concerning pattern, additional evaluation may be needed. That may include repeat labs, blood gas analysis, review of medications or toxins, and assessment for infection, kidney problems, or other underlying causes. In short, use the calculator as part of a wider clinical assessment, not as a isolated answer.
Frequently Asked Questions
What is the anion gap formula?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate: anion gap = sodium - (chloride + bicarbonate). This formula is the core of most calculator tools and is used to assist acid-base interpretation.
What is a normal anion gap value?
A normal anion gap value depends on the lab’s reference range and measurement method. Many laboratories report a normal range in the low teens, but laboratory variation is typical, so the report’s listed interval should be used for interpretation.
How can you calculate the anion gap from sodium, chloride, and bicarbonate?
To work out the anion gap, combine chloride and bicarbonate together, then deduct that total from sodium. As an example, if sodium is 140 mEq/L, chloride is 104 mEq/L, and bicarbonate is 24 mEq/L, the result is 12 mEq/L. An anion gap calculator does this automatically.
Why does a low albumin level affect the anion gap?
Albumin is a important unmeasured anion in the blood. When hypoalbuminemia is present, the measured gap may look lower than expected, which is why albumin correction is sometimes needed. A corrected anion gap gives a better estimate of the real acid-base picture.
Which conditions cause a high anion gap?
A high anion gap is often associated with metabolic acidosis from conditions such as lactic acidosis, ketoacidosis, and toxic alcohol ingestion. These causes elevate unmeasured acids in the blood and can suggest a serious problem that needs urgent evaluation.