What Is the Meaning of the Anion Gap?
The anion gap is a test-derived value that helps clinicians evaluate electrolytes and identify an acid-base imbalance. It is computed from common blood chemistry results, especially sodium, chloride, and bicarbonate. Because it shows the balance of measured ions in the blood, the anion gap can serve as a useful diagnostic clue during metabolic acidosis evaluation.
In simple terms, the anion gap contrasts the positively charged ions and negatively charged ions reported on an electrolyte panel. Most commonly, the calculation uses serum sodium as the main measured cation, then subtracts serum chloride and serum bicarbonate. The resulting anion gap result helps differentiate between different causes of acidosis and supports further lab interpretation.
An anion gap calculator speeds up this process by applying the standard equation automatically. That is helpful because the value itself is only part of the picture; the real value comes from understanding what the number suggests about electrolyte balance and the likely cause of the patient’s symptoms or test result.
Anion Gap Formula and Input Values
The standard anion gap formula reads:
Anion gap = sodium - (chloride + bicarbonate)
Typical calculation tools ask for three inputs: sodium, chloride, and bicarbonate. These values usually come from a standard blood panel or comparable blood test. When added, the calculator provides the anion gap and helps support a more informed clinical assessment.
Some systems may include potassium in a different version of the equation, but the most common bedside and online approach relies on sodium, chloride, and bicarbonate. That makes the calculation useful for fast blood chemistry review and routine lab interpretation.
To use an anion gap calculator properly, make sure the numbers are from the same sample and expressed in compatible units, typically mEq/L. If the lab reports values in another format, convert them before calculating to avoid an incorrect result.
How to Calculate the Anion Gap Step-by-Step
To calculate anion gap manually, begin with the three values from the electrolyte test panel. Then use the formula in order. A thorough step-by-step approach reduces errors and improves the consistency of the test result.
Step 1: Identify the serum sodium value.
Step 2: Locate the serum chloride value.
Step 3: Locate the serum bicarbonate value.
Step 4: Sum chloride and bicarbonate together.
Step 5: Take away that total from sodium.
Here is a simple calculation example:
If the test values are sodium 140 mEq/L, chloride 104 mEq/L, and bicarbonate 24 mEq/L, the calculation is:
140 - (104 + 24) = 140 - 128 = 12 mEq/L
In this example, the anion gap is 12 mEq/L, which is often within a normal reference range depending on the laboratory. This kind of worked example is useful because it shows how the numbers on a blood test become a useful diagnostic clue.
When using an online calculator, the same steps happen instantly. Still, understanding the arithmetic helps you verify the output and connect it to the broader picture of electrolyte balance and acid-base disorder.
Normal Anion Gap Range and Reference Values
The normal range for the anion gap depends on the laboratory and the measurement method used. There is no single standard reference range, which is why clinicians interpret the result in context rather than relying on one fixed cutoff.
Many labs report a normal anion gap in a range that is roughly around the low teens, but the exact value can shift with assay differences and laboratory variation. Because of that, it is best to match the test result with the specific reference interval shown on the blood test report.
Albumin also matters. Since albumin is an unmeasured anion, low albumin can reduce the apparent gap and make a high-gap problem more likely to be overlooked. That is one reason a result should always be interpreted using both the numeric value and the surrounding clinical context.
If the value sits near the upper end of the normal reference range, it may still warrant attention in a patient with symptoms or other lab abnormalities. A borderline test result can give a useful diagnostic clue even when it does not definitely go beyond the range.
How a Raised Anion Gap Can Indicate
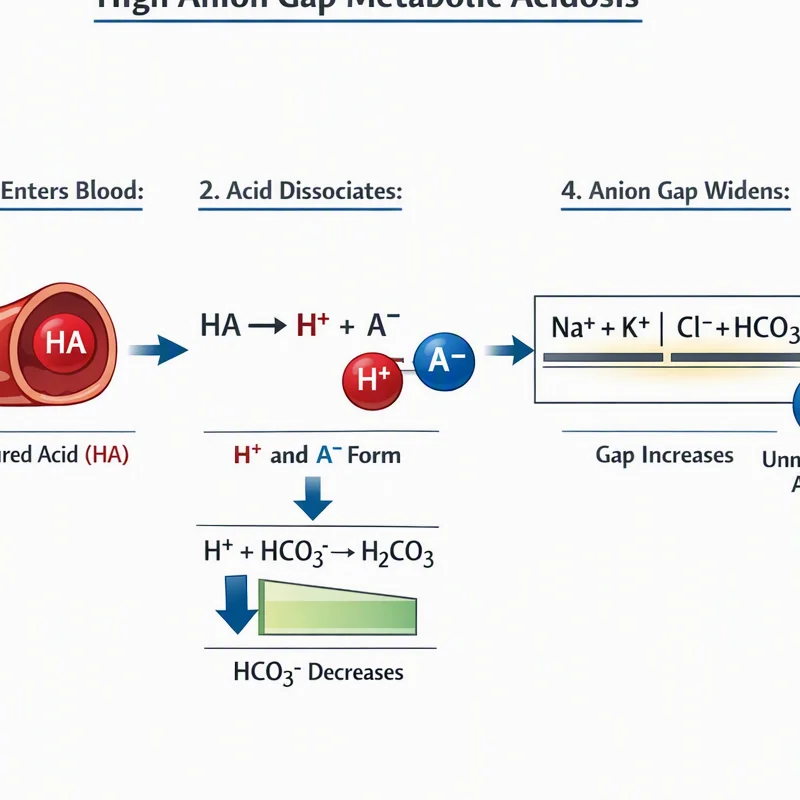
A raised anion gap often suggests normal anion gap limits an acidic blood state from the accumulation of undetected acids in the blood. This finding is also called high gap acidosis, and it can be an key warning sign that additional testing is needed.
Typical causes include lactic acidosis, ketoacidosis, and toxic alcohol ingestion. Each of these conditions shifts the blood chemistry in a different way, but all can increase the anion gap by adding acid or acid-like substances that are not directly counted in the standard panel.
Lactate-related acidosis may occur when tissues do not receive enough oxygen or when severe illness disrupts normal metabolism. Ketoacidosis can occur in uncontrolled diabetes, prolonged fasting, or other states of excess fat breakdown. Toxic alcohol ingestion is another serious cause that can create dangerous acid-base changes and requires urgent evaluation.
When the anion gap is elevated, the number alone does not reveal the cause. Instead, it acts as a key clue that prompts a broader review of symptoms, vital signs, medication history, and additional laboratory results. That is why the value is most useful as part of a structured medical evaluation.
Understanding a Normal Anion Gap
A result that is normal or close to normal does not exclude acid-base issues. In reality, normal anion gap acidosis may still point to clinically important disease. This pattern is often called non-anion gap metabolic acidosis or non-gap acidosis.
Typical causes include diarrhea, renal tubular acidosis, and hyperchloremia. Under these conditions, bicarbonate is reduced, but chloride increases to preserve electrical balance, so the calculated gap may stay within the normal reference range.
Diarrhea may cause bicarbonate loss from the gastrointestinal tract. Renal tubular acidosis impairs the kidneys’ ability to process acid or bicarbonate properly. Hyperchloremia, which means an elevated chloride level, can reflect the body’s compensation for bicarbonate loss or another underlying condition.
Because of this, a normal gap should not be read as “everything is fine.” It simply suggests a different pattern of acid-base disorder. Careful electrolyte interpretation and review of the broader blood test results are still essential.
Albumin Compensation and Modified Anion Gap
Albumin adjustment is essential because reduced albumin can make the measured value seem lower than it truly actually is. When low albumin is present, the raw number may downplay the degree of unmeasured acids in the blood. In those cases, a corrected anion gap can offer a more reliable estimate.
Albumin carries a negative charge and accounts heavily to the body’s unmeasured anion pool. If albumin is lowered, the gap may fall even if an acid load is present. This is why many clinicians follow an albumin-adjusted approach, especially when assessing unexplained acidosis.
The exact correction method can vary by institution, but the principle is the same: modify the result based on the albumin level so the adjusted value better matches the patient’s actual acid-base status. This can avoid a missed diagnosis in someone whose lab test shows low protein levels.
Serum total protein may also help contextualize the result, although it is not used directly in the standard equation. Alongside albumin, it can support a more comprehensive view of the patient’s biochemical state and strengthen the quality of lab interpretation.
How to Use the Anion Gap Calculator Safely
An anion gap calculator is a practical resource, but it should be used as part of thoughtful electrolyte interpretation. The number is only useful when you consider the clinical context, the patient’s complaints, and the balance of the blood chemistry.
Before depending on the result, verify that the inputs come from the same electrolyte panel and that units are aligned. If the sodium, chloride, or bicarbonate values are stale or inconsistent, the calculated number may be deceptive. Good lab interpretation depends on accurate, recent data.
It is also essential to avoid overinterpreting a one test result. A normal result does not exclude severe illness, and an elevated result does not reveal the cause by itself. The calculator is best understood as a assistive tool for medical disclaimer purposes: it can help direct thinking, but it does not replace professional judgment or formal diagnosis.
If the result suggests metabolic acidosis or another concerning pattern, additional evaluation may be needed. That may include repeat labs, blood gas analysis, review of medications or toxins, and assessment for infection, kidney problems, or other underlying causes. In short, use the calculator as part of a wider clinical assessment, not as a stand-alone answer.
Frequently Asked Questions
What is the anion gap formula?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate: anion gap = sodium - (chloride + bicarbonate). This formula is the core of most calculator tools and is used to assist acid-base interpretation.
What is a normal anion gap value?
A normal anion gap value depends on the lab’s reference range and measurement method. Many laboratories report a normal range in the low teens, but laboratory variation is common, so the report’s listed interval should be used for interpretation.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
In order to calculate anion gap, combine chloride and bicarbonate together, then take away that total from sodium. For example, if sodium is 140 mEq/L, chloride is 104 mEq/L, and bicarbonate is 24 mEq/L, the result is 12 mEq/L. An anion gap calculator calculates it automatically.
Why does a low albumin level affect the anion gap?
Albumin is a major unmeasured anion in the blood. When hypoalbuminemia is present, the measured gap may seem lower than expected, which is why albumin correction is sometimes needed. A corrected anion gap offers a better estimate of the real acid-base picture.
What conditions cause a high anion gap?
A high anion gap is often associated with metabolic acidosis from conditions such as lactic acidosis, ketoacidosis, and toxic alcohol ingestion. These causes increase unmeasured acids in the blood and can indicate a serious problem that needs urgent evaluation.