What Is the Anion Gap?
The anion gap is a derived value used to assist with interpreting acid-base disorders and spot unexpected shifts in serum electrolytes. It is usually derived from standard lab data on a basic metabolic panel and is based on the main measured ions: sodium, chloride, and bicarbonate.
At a clinical level, the anion gap shows the difference between positively charged and negative components in blood. Because many ions are not directly measured on standard tests, the calculation helps clinicians estimate whether extra acids or other unmeasured ions may be present. This makes it helpful in the evaluation of metabolic acidosis and broader acid-base balance.
In simplified form, the anion gap calculation compares sodium against chloride and bicarbonate. A higher-than-expected result may suggest a accumulation of acids, while a low or normal result does not always mean the body is free of metabolic derangement. That is why clinical interpretation matters as much as the number itself. An Anion Gap Calculator can speed up the delta ratio mixed acid base guide arithmetic, but it cannot take the place of medical assessment of the underlying pathophysiology.
The reason Albumin Influences the Anion Gap
Albumin is the most abundant protein in plasma and one of the key negatively charged proteins in the bloodstream. Because of its charge, albumin adds greatly to the pool of unmeasured anions that help determine the normal anion gap. In other words, part of the “missing” charge in the formula is normally supplied by serum protein, especially albumin.
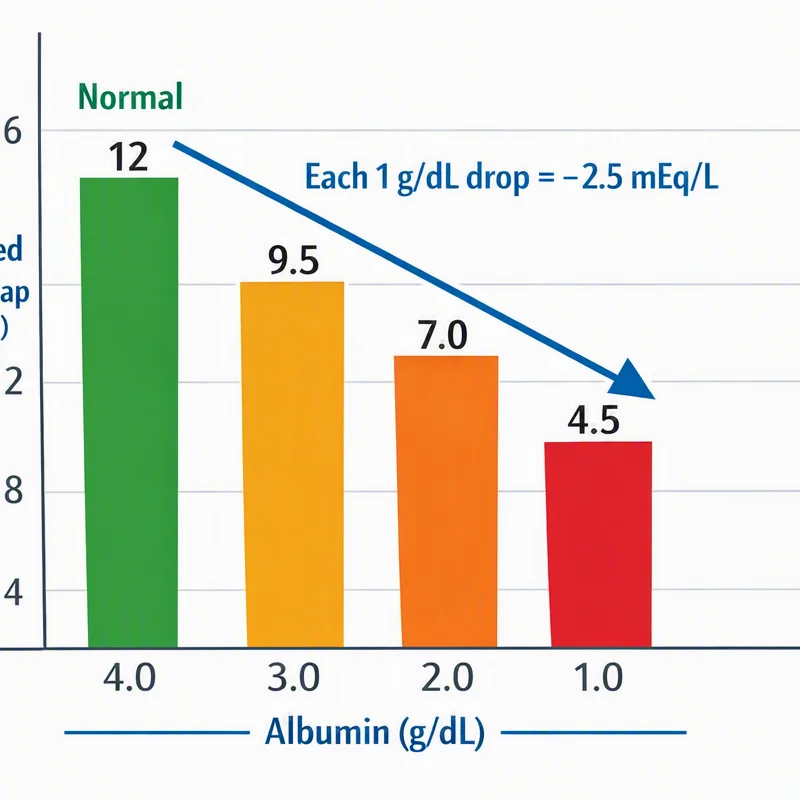
When serum albumin concentration drops, the body has less negatively charged particles contributing to the expected baseline. That means the measured anion gap may look lower than it actually is, even if an acid load is present. This is where protein binding and unmeasured electrolytes become important to clinical interpretation.
The relationship is direct: lower albumin tends to decrease the observed anion gap, while higher albumin can elevate it. Since the standard reference interval assumes typical albumin levels, any major deviation can alter the result. That distortion can obscure the true state of the patient’s acid-base status and obscure a meaningful gap.
Why Albumin Correction Is Needed
Hypoalbuminemia is a typical reason the anion gap becomes deceptive. When albumin is low, the measured value may decrease into the normal range even when unmeasured acids are increasing. This is why clinicians often calculate a corrected anion gap rather than counting only on the unadjusted result.
Albumin correction enhances acid-base interpretation by accounting for a major variable that alters the baseline. Without this adjustment, a patient with true high anion gap metabolic acidosis may be misclassified as having a normal gap disorder or no gap disorder at all. That can delay recognition of serious disease.
The goal is clinical accuracy. A corrected result helps reveal whether there is a hidden increase in unmeasured anions. This matters because the difference between a normal laboratory values pattern and a true elevated gap can change the entire diagnostic pathway, especially in acute illness.
How to Calculate the Anion Gap for Albumin
The formula for albumin correction updates the measured anion gap based on the patient’s blood albumin. The concept is clear: because albumin contributes to the normal gap, each decrease in albumin requires a necessary increase in the interpreted result. Many clinicians use a correction factor tied to the variation from the usual normal range.
A commonly used approach includes a set amount to the anion gap for every reduction in albumin below normal. The exact formula may change by institution, but the purpose is the same: restore the gap to what it would likely be if albumin were normal. This is where an anion gap calculator can be especially valuable, because it can carry out the anion gap calculation and apply the albumin adjustment quickly.
In practice, the clinician enters the measured sodium, chloride, bicarbonate, and serum albumin. The calculator then derives the corrected value, helping minimize errors in bedside interpretation. This process supports better medical assessment, especially when a low albumin level might otherwise obscure clinically important abnormalities.
When a Normal Anion Gap Can Be Misleading
A regular gap does not always mean there is no significant acid problem. In fact, metabolic acidosis may still be present even when the anion gap appears normal if albumin is low. This can create concealed acidosis, where the expected rise in gap is blunted by low albumin.
This issue is particularly important in patients with lactic acidosis or ketone acidosis. Both conditions can produce a true rise in unmeasured acids, but the gap may look deceptively ordinary if albumin is depressed. In those cases, the corrected anion gap may reveal an unrecognized high anion gap acidosis that would otherwise be missed.
That is why clinicians should not stop at the uncorrected number. The broader clinical picture matters, including the patient’s symptoms, vital signs, and other lab markers. A simple “normal” result can hide substantial metabolic derangement, especially if the underlying process is rapidly evolving or mixed with other disorders.
Frequent Reasons of Decreased Albumin
A number of conditions can lower albumin and consequently skew the anion gap. Liver disease may impair albumin synthesis, resulting in lower circulating levels over time. Because the liver makes albumin, chronic hepatic dysfunction often has a clear effect on the serum protein balance that maintains the normal gap.
Nephrotic syndrome can lead to major urinary loss of albumin, which reduces the serum albumin concentration and changes the expected anion gap. In malnutrition, reduced protein intake and poor overall nutritional status can also cause hypoalbuminemia. These changes may be gradual, but they have significant consequences for interpretation of blood chemistry.
Inflammation is another common cause. During acute or chronic inflammatory states, albumin often declines as part of the body’s response. Because inflammation is frequent in hospitalized and critically ill patients, albumin correction is often essential for precise clinical interpretation in real-world settings.
In what way do Clinicians Apply the Corrected Anion Gap
Clinicians use the corrected anion gap as part of the workup for acid-base disorders. It is not used in isolation; rather, it is interpreted alongside history, physical findings, and test results such as the arterial blood gas and basic metabolic panel. Together, these data help determine whether a patient has an elevated gap, a normal gap, or a mixed process.
The corrected result can change clinical decision-making in important ways. For example, if the uncorrected gap looks normal but the corrected value is elevated, the clinician may investigate more thoroughly for toxins, tissue hypoperfusion, renal dysfunction, or other causes of acid buildup. This is especially useful when the patient appears ill but the standard numbers seem reassuring.
Albumin correction also supports better recognition of compensatory changes. A patient may show partial compensation on blood gas testing, and the corrected gap helps determine whether the compensation is appropriate or whether another hidden disorder is present. This improves diagnostic accuracy and helps clinicians avoid premature closure.
Pitfalls and Challenges of Albumin Correction
Although albumin correction refines interpretation, it is imperfect. Laboratory variation can affect sodium, chloride, bicarbonate, and albumin measurement, which means minor differences between labs may affect the calculated result. This is one reason the corrected anion gap should always be interpreted in context.
Another challenge is the mixed acid-base disorder. A patient may have more than one process occurring at once, such as lactic acidosis along with vomiting-related alkalosis or renal compensation. In these situations, the corrected gap may suggest a hidden acidosis, but it may not fully explain the entire pattern. Additional tools like the delta gap can help identify whether the rise in gap matches the fall in bicarbonate.
There are broader diagnostic limitations. The albumin correction formula is an estimate, not a direct measurement of all unmeasured ions. Other abnormalities in protein binding, inorganic ions, or the patient’s overall metabolic state may influence the result. For that reason, clinicians should use the corrected number as one piece of the full acid-base evaluation, not as the sole answer.
FAQs About Albumin Correction and the Anion Gap
Why does low albumin lower the anion gap?
Low albumin reduces the anion gap because albumin normally provides a large share of the blood’s unmeasured anions. When albumin falls, there are fewer negatively charged particles in the serum, so the calculated gap decreases even if the true acid-base status has not improved. This is why hypoalbuminemia can make the anion gap look deceptively normal.
How do you correct the anion gap for albumin?
You use an albumin correction formula that adjusts the measured anion gap based on the patient’s serum albumin. In practice, the correction adds a set amount for each unit that albumin falls below the usual reference range. An anion gap calculator can automate the arithmetic, but the clinician still needs to interpret the corrected number in the context of the patient’s overall condition.
When should correction for albumin be applied?
Albumin correction should be applied anytime albumin is reduced or suspected to be low, especially in patients with metabolic acidosis, suspected high anion gap metabolic acidosis, or abnormal acid-base findings. It is especially helpful when assessing critically ill patients, because hypoalbuminemia is frequent and can conceal a genuine increase in acid burden.
Can a normal anion gap hide a serious acidosis?
Yes. A normal anion gap can conceal serious acidosis when low albumin masks the increase in unmeasured anions. This can occur with lactic acidosis, ketoacidosis, and other sources of occult high anion gap acidosis. A corrected value often reveals the hidden process and strengthens acid-base balance assessment.
Is an anion gap calculator enough without albumin correction?
Not usually. An anion gap calculator is useful for the initial calculation, but without albumin correction it may fail to detect important abnormalities in patients with low albumin. For accurate clinical interpretation, the calculator should incorporate or be followed by albumin adjustment. That approach enhances diagnostic accuracy and helps clinicians avoid overlooking hidden acid-base disorders.