What is the anion gap?
The anion gap is a derived value that helps clinicians assess the balance of electrolytes in the blood. It is typically derived from the main ions measured on a basic metabolic panel, especially sodium, chloride, and bicarbonate. Because routine lab tests do not measure every charged particle in the blood, the anion gap suggests the amount of unmeasured anions present.
In plain terms, the anion gap helps indicate whether something is missing from the expected acid-base balance. A low or high result does not establish a condition by itself, but it acts as an useful diagnostic clue in the emergency setting. That is why an anion gap calculator is often used as soon as blood chemistry results are available.
The calculation is often based on the difference between positively charged sodium and the sum of chloride plus bicarbonate. Since bicarbonate is a key buffer, changes in its level often reflect a metabolic derangement that needs rapid attention. Emergency clinicians use this value to identify an acid-base disorder before the cause is fully known.
The reason emergency medicine clinicians rely on an anion gap calculator
ED practice depends on fast clinical pattern spotting. The anion gap calculator enables clinicians quickly determine whether a patient may have metabolic acidosis, a potentially serious form of acidemia that can occur in critical illness. It is not merely a number; it is a tool for clinical decision-making.
If a patient presents with confusion, tachypnea, hypotension, or suspected toxin exposure, the anion gap can focus the differential diagnosis. Along with an arterial blood gas and a basic metabolic panel, it helps determine whether the patient has a primary acid-base problem and whether compensation is appropriate. The result can influence triage, the need for repeat labs, and whether advanced critical care support is needed.
The anion gap is especially helpful because it can provide a faster signal than waiting for a complete workup. If the anion gap is elevated, clinicians may immediately consider lactic acid elevation, ketone production, renal dysfunction, or toxic ingestion. If it is normal, they may shift attention to bicarbonate loss, chloride excess, or a mixed process. That rapid sorting makes the tool valuable in the first minutes of evaluation.
High anion gap vs normal anion gap: what is the difference?
A high anion gap implies that additional acids or acid-related compounds are building up in the blood. This often happens when there is increased production of acids or decreased clearance of them. Common causes include lactic acidosis, ketoacidosis, and renal failure.
In lactic acidosis, excess lactate builds up when tissues do not receive sufficient oxygen or are unable to use oxygen effectively. In ketoacidosis, the body creates ketones when it cannot use glucose properly. In renal failure, acid removal is limited, which allows acid compounds to accumulate.
A normal anion gap, sometimes called a non-gap metabolic acidosis, usually points to bicarbonate loss with a compensatory rise in chloride. This is frequently called hyperchloremic acidosis. In this pattern, the blood may still be acidic, but the missing bicarbonate is replaced by chloride rather than by unmeasured acids. That difference is important because it changes the likely etiology and next tests.
Emergency clinicians use the distinction between high and normal anion gap to direct the workup quickly. A high gap often signals acid accumulation from severe systemic disease or toxin exposure, while a normal gap may suggest gastrointestinal bicarbonate loss or renal tubular problems. In both cases, the anion gap is not the final answer, but it helps identify the direction of the search.
Common critical triggers of an elevated anion gap
Several urgent conditions can produce an elevated anion gap, and some require immediate treatment. Among the most important are sepsis, shock, toxic alcohols, and salicylate poisoning. Each can create a critical metabolic state that calls for rapid recognition.
Sepsis can lead to lactic acid buildup when infection leads to poor perfusion and impaired oxygen delivery. Shock from any cause can do the same because of tissue hypoperfusion, which promotes anaerobic metabolism and lactate production. In these settings, the anion gap may be an early warning sign that the patient is worsening even before the full picture is clear.
Toxic alcohols such as methanol or ethylene glycol can cause a marked high anion gap through toxic metabolites. These cases are time-sensitive, and early lab interpretation may be the first clue that a poisoning is present. Salicylate poisoning can also lead to an elevated gap and a complex acid-base pattern, sometimes including respiratory alkalosis and metabolic acidosis together.
Because these causes are potentially life-threatening, an increased anion gap should trigger immediate attention to the patient’s symptoms, vital signs, and exposure history. The Anion Gap Calculator helps clinicians move from a vague complaint https://penzu.com/p/f79b52c0950c4932 to a focused list of dangerous possibilities.
How to interpret the anion gap in clinical context
Interpreting the anion gap requires more than checking a single number. Albumin plays a major role because it is a negatively charged protein that strongly affects the gap. If albumin is low, the measured anion gap may appear falsely normal or only mildly elevated even when important acids are present.
That is why a corrected anion gap is often more informative than the raw value. Adjusting for albumin improves lab interpretation and helps reduce missed diagnoses in patients with critical illness, malnutrition, liver disease, or inflammation. A lower albumin level can obscure a clinically important acid load.
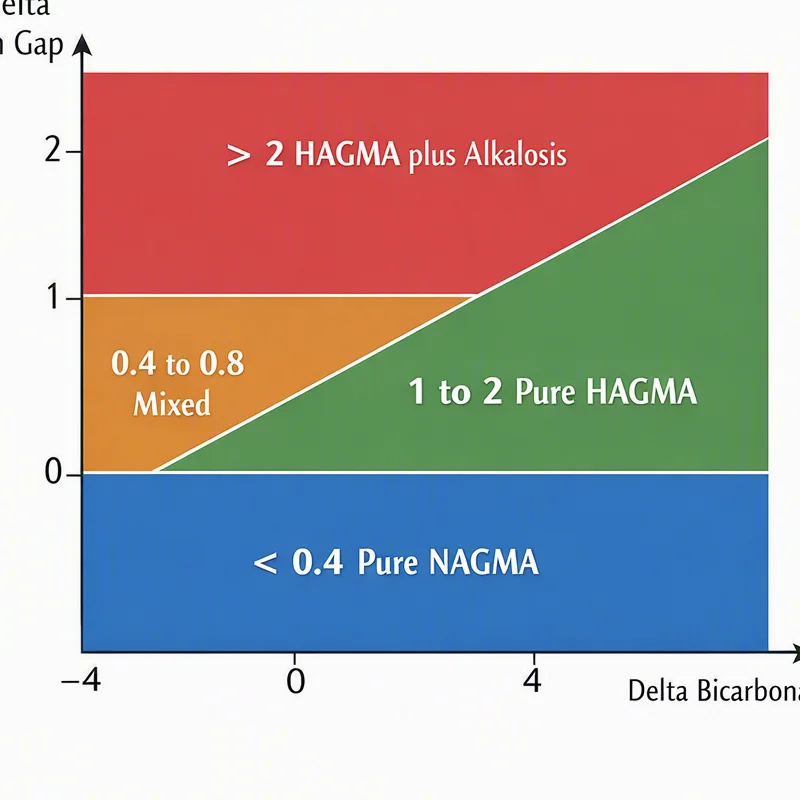
Another useful concept is the delta gap, which compares against the change in anion gap to the change in bicarbonate. This helps reveal whether another acid-base disorder is also present. For example, a patient may have a high anion gap metabolic acidosis plus a second process such as metabolic alkalosis or normal-gap acidosis.
The broader picture also includes the rest of the lab values. A rising creatinine may support renal failure, a high lactate can support tissue hypoperfusion, and positive ketones can support ketoacidosis. The anion gap is strongest when it is considered alongside the patient’s symptoms, history, exam findings, and full electrolyte picture.
When a normal anion gap can still be dangerous
A typical anion gap does not mean stability. Significant illness can still be occurring even if the number appears comforting. For example, diarrhea can cause significant bicarbonate loss and a normal-gap metabolic acidosis that results in acidemia. The patient may be critically unwell despite a gap that is not elevated.
Renal tubular acidosis is another important cause of normal anion gap acidosis. In this condition, the kidneys cannot effectively manage acid or bicarbonate handling. Patients may present with weakness, dehydration, or electrolyte abnormalities that need treatment even though the anion gap does not stand out.
A mixed acid-base disorder can also hide a dangerous process. One disorder may raise the gap while another lowers it, creating a value that looks normal on paper. For example, a patient may have lactic acidosis plus metabolic alkalosis, or a high-gap process plus chloride-driven acidosis. In such cases, the anion gap alone can overlook the full picture.
Chloride is central to recognizing these cases because increased chloride often accompanies bicarbonate loss. If the clinician only sees a normal anion gap, the underlying problem may be ignored. This is why the electrolyte pattern must always be read as a single unit, not in isolation.
Why the anion gap is helpful for prioritization and treatment decisions
In emergency care, the anion gap helps clinicians decide who needs quicker escalation. A strongly elevated gap may suggest a critical process requiring immediate assessment in critical care. Before even the exact cause is known, the result can justify swift testing, ongoing monitoring, or ICU-level concern.
The gap also supports early diagnosis. If the clinical picture suggests infection, shock, diabetic crisis, poisoning, or renal failure, the anion gap helps reveal that a metabolic process is underway. This can expedite treatment choices such as fluid resuscitation, toxin-specific therapy, insulin, dialysis consultation, or repeat review of acid-base status.
For monitoring, serial anion gaps can help track whether a treatment is effective. If the cause is corrected, the gap may improve as the underlying acid load falls. That trend can be especially valuable in patients with acidemia who are too unstable to wait for slower clinical changes.
Because the anion gap is available from common chemistry testing, it is a practical tool for bedside decisions. It does not replace the exam or more advanced testing, but it gives emergency teams a fast way to identify the sickest patients and to direct the next diagnostic step.
Limitations of anion gap interpretation
Even though valuable, the anion gap is not foolproof. A lab error can create a inaccurate result, which is why a repeat test is sometimes necessary if the number does not match the overall clinical picture. Sample handling issues, contaminants, or transcription problems can all influence interpretation.
The specified normal range also matters. Different laboratories may use slightly different methods and normal values, so clinicians must read the result according to the reporting lab. A value that appears mildly abnormal in one setting may be normal in another.
The measure is also limited because it calculates only some of the chemical balance in the blood. Unmeasured anions may accumulate, but the tool cannot detect them directly. It can suggest their presence, yet it cannot name the exact substance causing the shift. That is why the anion gap is a clue, not a definitive answer.
In the end, the clinical setting always counts. Someone with vomiting, diabetes, kidney disease, suspected poisoning, or infection may need additional evaluation no matter whether the anion gap is elevated, normal, or borderline. The most accurate interpretation integrates the calculated value with symptoms, exam findings, and the broader metabolic picture.
Common questions about anion gap in emergency care
What can the anion gap tell you in emergency care?
The anion gap tells emergency providers whether there may be a hidden acid-base problem that is not obvious from standard chemistry alone. It is a rapid way to look for metabolic acidosis, unmeasured anions, and potential causes such as lactic acidosis, ketoacidosis, renal failure, or toxin exposure. In practice, it aids in refine the differential diagnosis and inform urgent next steps.
Why is the anion gap important for diagnosing metabolic acidosis?
The anion gap is important because it helps separate various types of metabolic acidosis. A high anion gap value suggests added acids are accumulating, while a standard anion gap indicates bicarbonate loss or chloride gain. This difference improves diagnostic value and assists clinicians target the correct cause more quickly.
Can a normal anion gap still signal a severe problem?
Absolutely. A standard anion gap can still be seen in significant illnesses such as gastrointestinal loss, renal tubular acidosis, or a mixed acid-base disorder. A patient may still have marked acidemia even if the gap is not elevated. That is why emergency medicine teams interpret the anion gap alongside patient complaints, lab values, and the overall clinical picture.
How does albumin affect the anion gap?
Albumin lowers or raises the expected anion gap because it is a major unmeasured anion in the blood. When albumin is low, the measured anion gap may appear misleadingly normal. A corrected anion gap adjusts for that effect and gives a more accurate estimate of the patient’s acid load.
What causes a high anion gap in the emergency setting?
Typical causes include lactic acidosis from sepsis or shock, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions can create a potentially life-threatening metabolic derangement that requires prompt recognition. The anion gap calculator helps clinicians notice the pattern early and direct the workup.