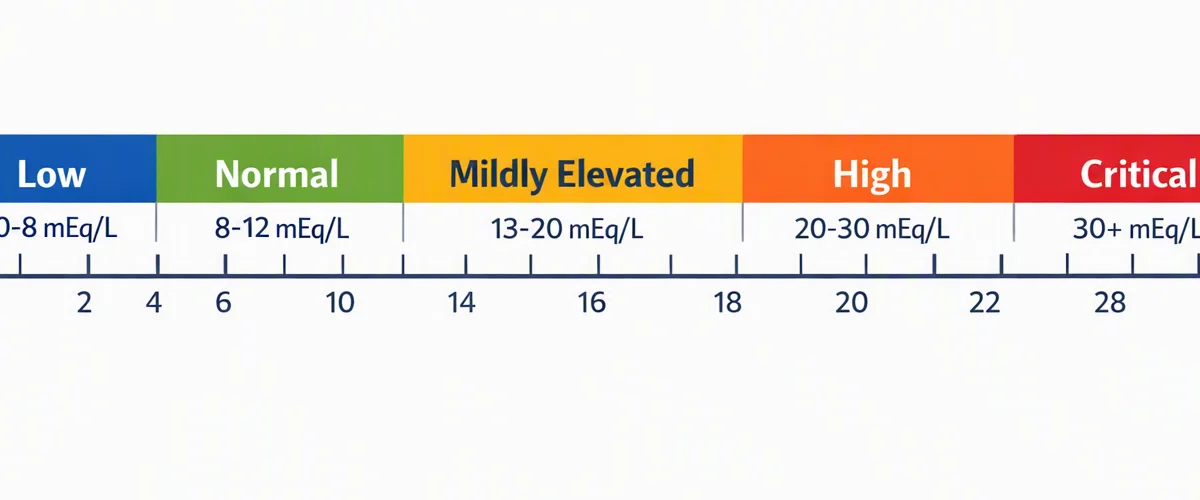
What Is the Anion Gap?
The anion gap is a calculated value that helps assess the balance of electricly charged particles in the blood. It is obtained from common serum electrolytes and is often used as a diagnostic marker in acid-base disorder evaluation. The most common version uses sodium, chloride, and bicarbonate to calculate the difference between measured ions and unmeasured electrolytes.
In simple terms, the anion gap examines the positively charged and negative-charge components found in usual blood chemistry. Because not every ion is directly measured, the gap can reveal hidden acids or other substances that may be affecting the body’s acid-base balance. This makes it especially useful in metabolic acidemia workups.
The standard formula for the anion gap is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians include potassium in the equation, but the most widely used version leaves it out. The result is usually expressed in mEq/L, and interpretation depends on the lab’s reference range or the expected range used by the clinician.
How come Fix the Anion Gap for Albumin?
Albumin is one of the primary negative-charge proteins in blood, so it has a significant effect on the calculated anion gap. When albumin is low, the measured gap can appear falsely normal or low even when a true acid-base problem is present. This is why hypoalbuminemia matters so much during acid-base interpretation.
Adjusting the gap for albumin improves accuracy because it accounts for the lost negative charge contributed by low serum albumin. In other words, the corrected anion gap gives a more realistic picture of the body’s acid load. This is especially important in patients with illness, inflammation, malnutrition, liver disease, or other conditions that decrease albumin.
A standard albumin correction factor is used to anion gap in chronic kidney disease estimate how much the gap should increase when albumin is below normal. The goal is to make the adjusted result more reliable for clinical decision-making. This is why an anion gap calculator often includes albumin as an input field.
Revised Anion Gap Formula
The usual anion gap formula reads:
Anion gap = Sodium − (Chloride + Bicarbonate)
To work out the albumin-corrected anion gap, include an adjustment for decreased albumin. A typical albumin correction is written as:
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − albumin in g/dL)
This formula sets 4.0 g/dL as a normal normal albumin value and applies 2.5 mEq/L for every 1 g/dL decrease in albumin below 4.0. The precise factor can change somewhat by source, but this version is widely used in practice. Always evaluate the result using your lab’s normal range and the medical context.
If potassium is included in a local protocol, the equation is expressed as:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
However, most calculators and clinical references depend on the sodium-based formula. The corrected value is still reported in mEq/L, and the purpose is to more easily detect a hidden high anion gap state when albumin is low.
Stepwise: How to Work Out Corrected Anion Gap
To calculate corrected anion gap by hand, use the basic lab data from the electrolyte panel. You need serum sodium, serum chloride, serum bicarbonate, and albumin level. These remain common laboratory values found in routine blood tests.
Apply this step-by-step formula:
- Step 1: Calculate the raw anion gap using sodium − (chloride + bicarbonate). Step 2: Compare the albumin result with the normal value, usually 4.0 g/dL. Step 3: Calculate the albumin deficit by the albumin correction factor, usually 2.5. Step 4: Add that number to the raw anion gap. Step 5: Review the corrected result with the expected range.
Example structure:
Raw anion gap = 140 − (104 + 24) = 12 mEq/L
Albumin correction = 2.5 × (4.0 − 2.0) = 5 mEq/L
Corrected anion gap = 12 + 5 = 17 mEq/L
This basic clinical calculation can change the interpretation significantly. A raw value that seems normal may become elevated once albumin is accounted for.
How an Anion Gap Calculator Operates
An anion gap calculator is an online calculator or clinical calculator that automates the math for you. It usually offers input fields for sodium, chloride, bicarbonate, and albumin. Some versions also support potassium, although it is not always necessary.
The calculator processes the lab values, applies the anion gap correction, and shows a corrected result. This makes it more efficient to evaluate blood chemistry in clinical settings where a quick result analysis is helpful. It also reduces the chance of arithmetic mistakes during busy workflows.
Most calculators present both the raw gap and the albumin-corrected anion gap. That dual output helps clinicians assess the unadjusted and adjusted numbers side by side. For users learning the concept, the calculator can also serve as an interpretation guide by showing whether the result falls into a normal or elevated range.
Understanding a Corrected Anion Gap That Is High or Normal
A raised anion gap usually points to the presence of extra unmeasured acids. This is a important clue in acid-base imbalance workup. Common causes include lactic acid accumulation, ketone acidosis, kidney failure, and toxic exposures.
If the corrected value is elevated, the clinician should consider a hidden acid load is present even if the raw gap looked normal. This is why the corrected number is such an important diagnostic marker. Low albumin can mask the severity of the acid-base problem, and albumin correction helps unmask it.
A normal anion gap after correction may suggest that the raw elevation was mostly attributable to low albumin. That does not rule out disease, but it modifies the interpretation. In contrast, a persistently high corrected result supports a true acid excess and may guide the next steps in the metabolic acidosis workup.
Helpful interpretation points:
- Raised corrected gap: consider hidden acids or excess unmeasured ions. Corrected gap in the normal range: the apparent elevation may be explained by hypoalbuminemia. Low albumin can allow a dangerous process look less abnormal than it really is.
Common Mistakes When Calculating the Corrected Anion Gap
One typical problem is a units conversion issue. Albumin may be reported in g/dL or g/L depending on the lab, and the formula only works correctly with the intended unit. Using the wrong unit can distort the result and produce a misleading number.
A further concern is using the wrong reference interval. Different laboratories may list slightly different normal intervals for anion gap, so the same number can be interpreted differently depending on the lab’s standards. Always compare the result with the local expected range.
Many users also forget to consider whether potassium is included. If a formula includes potassium in one setting but not another, the values will not match. That mismatch is a frequent formula error in hand calculations and in copied notes.
Common errors include:
- Applying the raw gap without albumin adjustment when albumin is clearly low. Entering bicarbonate instead of total CO2 without understanding the lab report. Assuming every calculator uses the same correction factor. Overlooking the clinical context of the blood chemistry.
Careful review of the inputs prevents misleading conclusions and improves the quality of the final interpretation.
Examples of Corrected Anion Gap Calculations
This is a sample calculation based on typical lab values. Use these values:
- Sodium = 138 mEq/L Chloride = 104 mEq/L Bicarbonate = 22 mEq/L Albumin level = 2.4 g/dL
First, determine the raw anion gap:
138 − (104 + 22) = 12 mEq/L
After that, work out the albumin correction:
2.5 × (4.0 − 2.4) = 4.0 mEq/L
Then, include the correction to the raw anion gap:
Corrected value = 12 + 4 = 16 mEq/L
This tells you that the adjusted result is higher although the raw anion gap was inside many labs’ normal range. Low albumin was masking part of the abnormality.
One more sample calculation:
- Serum sodium = 142 mEq/L Chloride = 100 mEq/L Bicarbonate = 26 mEq/L Albumin = 4.2 g/dL
Unadjusted anion gap = 142 − (100 + 26) = 16 mEq/L. As albumin is not low, minimal or no correction is needed. The corrected value remains basically the same, and the elevated gap is more apt to reflect a real increase in unmeasured acids.
When to Use a Corrected Anion Gap in Clinical Practice
A corrected gap is most helpful when the patient has hypoalbuminemia and an acid-base disorder is being evaluated. It is particularly helpful in critical care, where fluid shifts, inflammation, malnutrition, and organ dysfunction often lower albumin. In those cases, the raw result can be misleading.
It also matters in kidney disease, where https://privatebin.net/?ca33de4d51be27a8#8M3LihsihgzBiyfAofJZeCebGqmVojfaH8yQV4TAJrM1 acid retention can alter the electrolyte pattern and complicate interpretation. A corrected value can improve the diagnostic picture and help clinicians distinguish between different causes of acidosis.
Another important use is toxic ingestion evaluation. If a patient has unexplained acidosis, an elevated corrected gap may support the presence of hidden acids or toxic compounds. That can change urgent management decisions.
In clinical use, rely on the corrected value when:
- Albumin is below normal. You are concerned about metabolic acidosis. The initial anion gap looks normal or borderline despite concern. Clinical findings do not match the measured electrolyte pattern.
Used this way, the corrected value becomes a useful reference tool rather than just another number.
FAQ About Anion Gap Calculation
How can you calculate corrected anion gap from lab values?
First of all determine the original anion gap using sodium − (chloride + bicarbonate). Then correct for albumin using an albumin correction factor, usually 2.5 mEq/L for each 1 g/dL albumin below 4.0. This results in the corrected anion gap, which provides a more precise clinical calculation when albumin is low.
Why does low albumin change the anion gap?
Serum albumin is a major negatively charged protein in blood, so low albumin reduces the number of unmeasured negative charges. It can make the calculated anion gap appear lower than it really is. Albumin correction helps bring back the normal range and enhances acid-base interpretation.
What is the normal corrected anion gap range?
The typical corrected anion gap interval varies with the laboratory’s benchmark range, but many clinicians consider it to fall within the expected anion gap range after albumin adjustment. Because approaches differ, always read the result using the lab’s normal range and the patient’s overall clinical context.
Should potassium be included in the anion gap calculation?
Typically, potassium is not part of the standard formula used by most anion gap calculator tools. Some formulas do include potassium, but that is unusual. If potassium is included, the result will differ, so the method must be consistent with the reference or calculator you are using.
When is it appropriate to use a corrected anion gap be used instead of the raw anion gap?
Use the adjusted anion gap whenever albumin is low and you are evaluating an acid–base disorder, especially metabolic acidosis. The corrected value is more accurate in hypoalbuminemia because it takes into account hidden changes in unmeasured ions. It is especially useful in critical care, kidney disease, and toxic ingestion workups.