
What Does the Anion Gap Mean?
The anion gap is a calculated figure that aids in assessing the distribution of ions in the blood, especially when evaluating electrolytes and acid-base balance. It compares the main recorded cations, such as sodium, with the main measured anions, such as chloride and bicarbonate. Clinicians apply it as a quick way to detect patterns that may indicate an acid-base disorder.
Although the anion gap is not directly measured, it is calculated from common lab data. That makes it a useful diagnostic tool in a blood test or serum chemistry panel. Because the body’s unmeasured ions also play a role to the total, the anion gap can reveal hidden abnormalities in serum electrolytes even when individual values look only slightly abnormal.
In plain terms, the anion gap helps estimate whether there are extra acids in the bloodstream or whether bicarbonate has been lost. That is why it is often part of the metabolic panel used for clinical interpretation of symptoms like weakness, nausea, rapid breathing, or confusion.
How an Anion Gap Calculator Functions
An Anion Gap Calculator applies a straightforward anion gap formula derived from laboratory values from a serum chemistry panel. The usual equation is:
Anion gap = sodium − (chloride + bicarbonate)
Some versions also include potassium, especially in older formulas. In that case, the equation becomes sodium plus potassium minus chloride and bicarbonate. Most modern clinical settings use the simpler version because potassium usually contributes less to the final result than the other components.
To calculate anion gap correctly, the calculator needs a current sodium level, chloride level, and bicarbonate level. These values come from routine serum electrolytes testing. The result then helps determine whether the pattern fits a normal anion gap or suggests another cause of acid buildup.
The calculator is most useful when it is paired with context. A number by itself does not explain everything. The same result can mean different things depending on the patient’s symptoms, medications, kidney function, hydration status, and overall clinical interpretation. That is why the calculator should be viewed as a guide, not a standalone diagnosis.
Normal Anion Gap Range Outlined
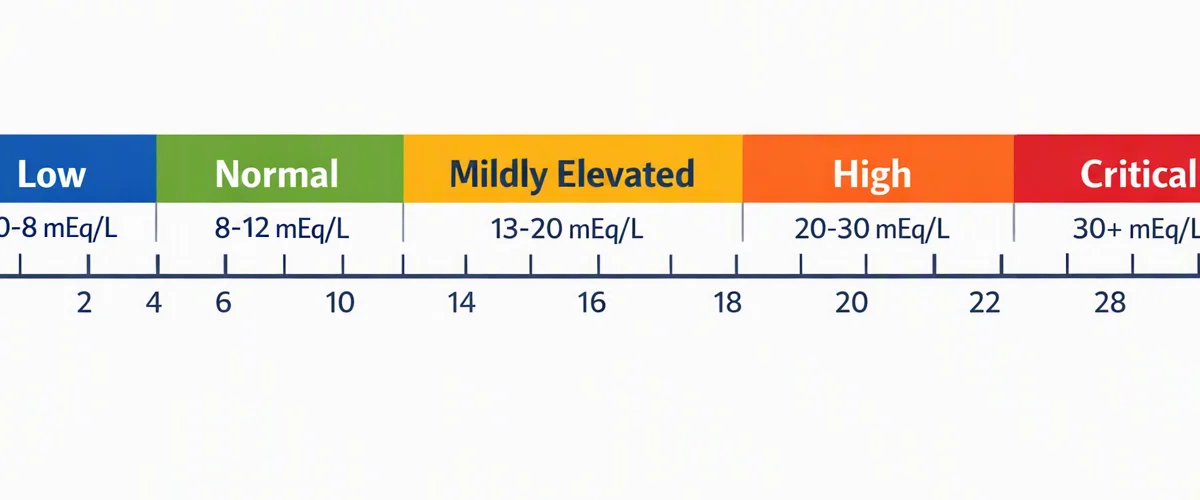
The usual range for the anion gap varies by the laboratory method and the local normal range. Different analyzers and calibration methods can produce slightly different values, so a result should always be read alongside the lab’s own reference range. In many settings, a common range is roughly between 8 and 12 mEq/L when potassium is excluded, but the exact cutoffs can vary.
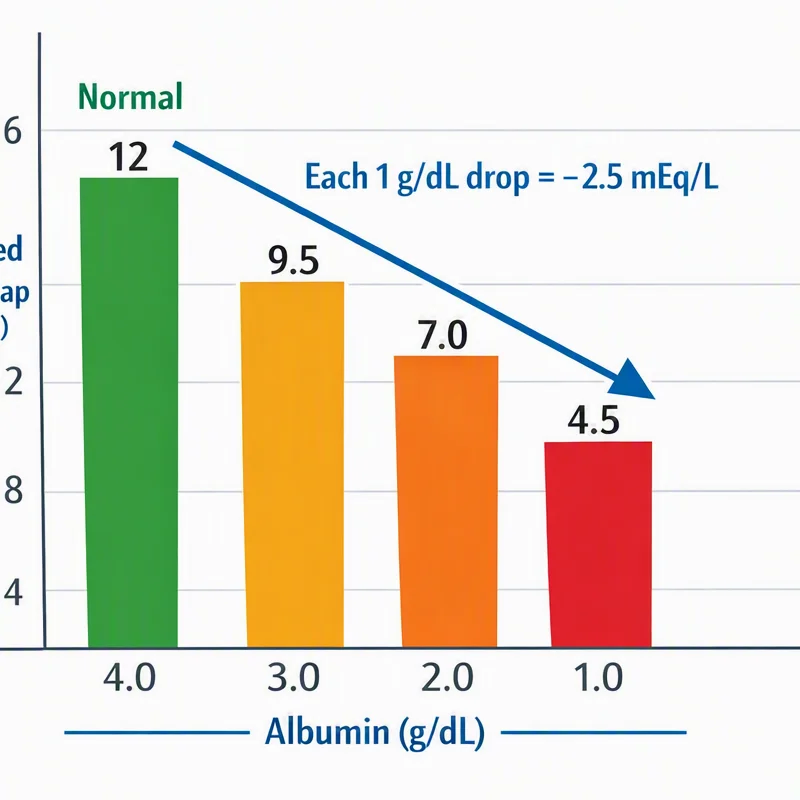
One reason the range varies is albumin. Albumin is a negatively charged protein that contributes to the unmeasured portion of the anion gap. If albumin is low, the measured gap may appear lower than expected even when the acid-base state is not truly normal. This is why albumin correction matters in certain cases.
A true normal anion gap usually suggests that there is no large accumulation of unmeasured acids. However, that does not automatically mean everything is normal. The result still needs to be interpreted in the context of acid-base status, kidney function, and other laboratory findings. A person may still have an illness even if the anion gap sits within the expected reference range.
For that reason, the anion gap should be seen as part of the broader picture of electrolyte status and lab results, not as a single definitive answer.
Interpreting a Standard Anion Gap
A normal anion gap is especially important when evaluating metabolic acidosis. If bicarbonate is low but the anion gap stays normal, the pattern often points to a non-anion gap form of metabolic acidosis. In this scenario, the body has depleted bicarbonate or kept chloride rather than accumulating a large amount of unmeasured acid.
Two common https://anion-gap-analyzer361.lucialpiazzale.com/anion-gap-calculator-with-potassium-included causes are renal tubular acidosis and gastrointestinal bicarbonate loss. Renal tubular acidosis occurs when the kidneys do not handle acid and bicarbonate properly. Gastrointestinal bicarbonate loss can happen with prolonged diarrhea or other digestive fluid losses. Both can lower bicarbonate while keeping the anion gap in the usual range.
Reading this result correctly is important for a proper workup for metabolic acidosis. A normal gap can help narrow the differential diagnosis and support further testing. It may prompt review of urine studies, kidney function, medication use, and fluid losses. In other words, the pattern matters as much as the number.
One useful way to think about it is this: when the anion gap is normal, the problem often lies in bicarbonate loss or chloride gain rather than hidden acid accumulation. That distinction is key to clinical interpretation and helps clinicians determine the most likely source of the disorder.
Elevated Anion Gap Versus Typical Anion Gap
A increased anion gap suggests that unmeasured acids are rising in the circulation. That is in contrast to a normal gap pattern, where bicarbonate loss or chloride retention is more probable. Knowing this contrast is one of the key reasons people use an Anion Gap Calculator when reviewing an electrolyte panel.
Typical causes of a increased anion gap include lactic acidosis, ketoacidosis, and toxic ingestions. Lactic acidosis may occur when tissues do not get enough oxygen or when metabolism is disrupted. Ketoacidosis can happen in uncontrolled diabetes, starvation, or alcohol-related illness. Toxic ingestions may involve substances that create acid or interfere with metabolism.
Conversely, a normal result points away from those classic high-gap causes and toward patterns such as non-anion gap metabolic acidosis. This comparison is clinically important because the next steps in care may differ substantially. For example, a high gap often leads to a search for acid overproduction or toxin exposure, while a normal gap may shift attention to renal or gastrointestinal losses.
Because of this difference, the anion gap is not just a number. It is a organized way to arrange electrolyte abnormalities and support more rapid, more focused decision-making.
Variables Influencing the Calculation
A number of issues can alter the outcome even when the original condition has not changed much. One major factor is hypoalbuminemia. Since albumin contributes negative charge, low levels can lower the measured gap. In that setting, a corrected anion gap can offer a more accurate picture of the acid base state.
Measurement units also matter. The calculator assumes matching lab units, and mixing units can cause misleading numbers. A minor change in the reporting format may lead to a very different-looking result if it is entered incorrectly. That is one reason the Anion Gap Calculator should be used carefully and checked against the actual lab report.
Lab error is another likely source of confusion. Sample handling, analyzer variation, and transcription mistakes can all affect the final number. If the result does not fit the clinical picture, repeating the blood test may be appropriate.
Because of these caveats, a low or seemingly normal value should not be interpreted in isolation. A corrected anion gap may be more revealing when albumin is abnormal, and the overall clinical picture should always inform the next step.
When to Consider Using an Anion Gap Calculator
An Anion Gap Calculator is most useful when a clinician is reviewing a blood test or electrolyte panel and needs help interpreting possible acid-base changes. It is particularly helpful when bicarbonate is low, when there are unexplained symptoms, or when the cause of an acid-base disorder is not obvious.
It can be used during a general clinical assessment to support faster pattern recognition. For example, if a patient has abnormal serum electrolytes on a serum chemistry panel, the calculator can help determine whether the pattern fits high-gap acidosis, normal-gap acidosis, or another imbalance. This makes it a practical part of bedside reasoning and laboratory review.
The calculator is also useful when reviewing serial labs over time. Changes in the anion gap may help show whether treatment is working or whether a condition is evolving. In that sense, it is not just a one-time number but a way to track electrolyte balance and acid-base trends.
Still, the calculator should support, not replace, a full medical evaluation. Symptoms, medications, kidney function, blood sugar, lactate, ketones, and albumin all matter. The best use of the tool is as one piece of a larger diagnostic process.
Common Questions
What is considered a normal anion gap value?
A normal anion gap value varies based on the lab’s reference interval and the technique used to assess blood electrolytes. Many laboratories use a range around 8 to 12 mEq/L without potassium, but the exact reference range can vary. Always interpret the finding with the lab’s own reference interval.
How do you calculate the anion gap?
The standard formula for anion gap is sodium minus the sum of chloride and bicarbonate. Some formulas also include serum potassium. An Anion Gap Calculator performs this calculation automatically using values from a serum chemistry panel. To determine the anion gap accurately, the input values must be correct and in the proper units.
What does a normal anion gap mean?
A normal result often means there is no major accumulation of unmeasured acids. In the setting of low bicarbonate, it may suggest hyperchloremic metabolic acidosis rather than a high-gap process. Common causes include RTA and intestinal bicarbonate loss. The result still needs full medical interpretation in context.
What are the causes of normal anion gap metabolic acidosis?
Common causes include tubular kidney acidosis, intestinal bicarbonate loss, and some forms of kidney dysfunction or medication-related acid-base changes. In these cases, bicarbonate is reduced, but the gap stays normal because chloride often rises to maintain balance. This pattern is a classic part of the workup for metabolic acidosis.
Why does albumin affect the anion gap?
The albumin level is a negatively charged protein that contributes to the unmeasured portion of the gap. When albumin is low, the anion gap may appear artificially lower, which is why hypoalbuminemia can mask a problem. A adjusted anion gap helps account for this and gives a more accurate estimate of the true acid-base status.