What Is Anion Gap?
The anion gap is a computed value used to help evaluate electrolytes and the body’s acid-base balance. It represents the gap between the main measured cations and opposing ions in the blood, especially sodium and chloride, along with bicarbonate. Since some ions are not directly measured on a standard blood chemistry panel, the anion gap can help detect changes in anion concentration that may indicate a metabolic disorder or other acid-base disorder.
Clinicians often use the anion gap as a diagnostic indicator and a screening tool during patient evaluation. It does not provide a diagnosis by itself, but it can signal that something is affecting serum levels and overall chemical balance. The key idea is simple: if the gap is elevated or lower than expected, the blood test results may warrant closer review in clinical interpretation.
At its core, the anion gap shows the presence of unmeasured anions in the blood. In many cases, those unmeasured ions become more relevant when the body is dealing with an acid load, kidney problems, or shifts in proteins such as albumin.
Anion Gap Calculator Method
An anion gap calculator commonly uses a simple formula using routine lab values. The most widely used calculation is:
Anion gap = Serum sodium − (Serum chloride + Serum bicarbonate)
That calculation formula examines measured sodium with the sum of bicarbonate and chloride. It helps indicate whether there may be excess acids or atypical ions affecting the blood. Because the formula relies on routine measurements, it is straightforward to apply once the values are available from a lab report.
Some labs and clinicians may use a somewhat different version that includes potassium, but the sodium-based version is the most common in everyday practice. When using any anion gap calculator, it is important to understand which lab reference approach is being used so the result is interpreted correctly.
The formula is useful because it turns a few routine numbers into a practical medical assessment of electrolyte balance. A high or low result can suggest an electrolyte imbalance that needs attention, especially if the patient has symptoms or abnormal blood test results.
How to Calculate Anion Gap Step-by-Step
To complete the calculation, beginning with the values from the blood chemistry panel:
- Serum sodium Serum chloride Serum bicarbonate
Then apply the formula:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
Below is a quick example. If serum sodium is 140 mEq/L, serum chloride is 104 mEq/L, and serum bicarbonate is 24 mEq/L, the calculation is:
140 − (104 + 24) = 140 − 128 = 12 mEq/L
That value may be within the expected normal range depending on the laboratory measurement method. The units are usually expressed in mEq/L. Because different instruments and lab methods can produce somewhat different results, the exact reference range should always be checked against the reporting laboratory.
When reviewing the result, the number alone is not enough. The broader interpretive context is important, including symptoms, medications, kidney function, and whether there is evidence of metabolic acidosis or another acid-base disorder.
Typical Anion Gap Values and Measurement Units
The usual range for anion gap depends on the laboratory and the measurement method used. Many labs report a benchmark range that is roughly in the low numbers to early teens when measured in mEq/L. However, there is no single universal cutoff that applies to every lab because laboratory values can vary based on technology and calibration.
That is why it is best to interpret the result alongside the lab’s own local reference. A value that appears borderline in one setting may be normal in another. Also, different formulas may produce slightly different totals, which can affect how a result is categorized.
For practical use, the anion gap should be viewed as a trend as well as a single number. Repeated changes in the result may be more meaningful than one isolated value, especially if the patient’s lab levels are shifting over time.
Why a High Anion Gap Means
A elevated anion gap often implies https://anion-gap-test959.iamarrows.com/can-lithium-use-affect-the-anion-gap that extra acids are accumulating in the body, which can point toward acid buildup. In this setting, the blood contains additional extra negative ions that are not captured by the routine electrolyte panel. This is why the result is such a useful clinical clue in a clinical evaluation.
Common causes include lactate-related acidosis, where lactic acid rises during poor tissue oxygenation, shock, or severe illness, and ketone-related acidosis, where ketones accumulate, often in diabetes, starvation, or alcohol-related states. Both conditions create an acid load that increases the gap.
A elevated result may also be seen in renal failure, because the kidneys may not clear acids effectively. In some cases, a toxin ingestion can raise the anion gap as well. The pattern should always be matched with symptoms, other lab data, and the overall medical interpretation.
In short, a high anion gap does not tell you the exact cause, but it does alert clinicians to a likely metabolic disorder affecting acid handling or electrolyte balance.
How the Low Anion Gap Means
A reduced anion gap is not as common than an elevated one, but it can still be important. One major cause is hypoalbuminemia, because albumin is a negatively charged protein that plays a role in the measured balance of ions. When albumin falls, the gap may decrease even if the underlying acid-base status has not altered greatly.
Another possible explanation is lab error. Since the calculation depends on three individual measurements, any mistake in serum sodium, serum chloride, or serum bicarbonate can change the final result. That is why a very unexpected low value often needs repeat testing or a careful review of the original blood test results.
In rarer cases, a low result may reflect unusual proteins or other analytical issues. Because the number can be influenced by so many elements, it should be interpreted as part of the full clinical interpretation rather than as a standalone finding.
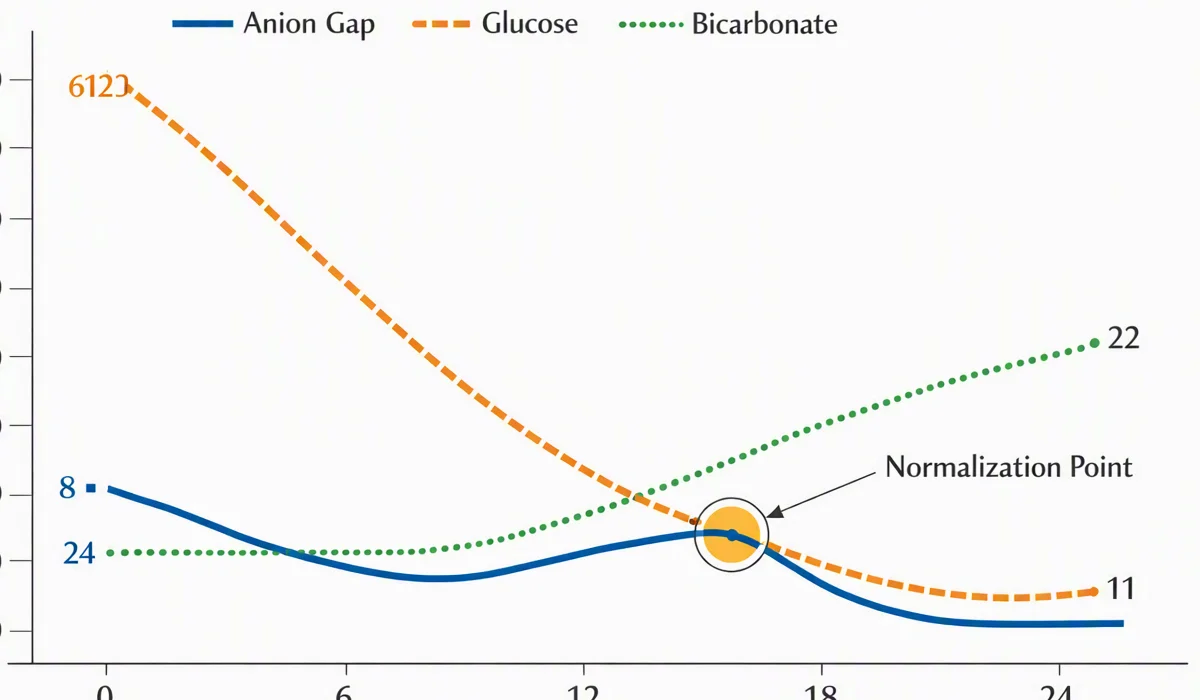
Corrected Anion Gap & Albumin Correction
Since albumin has a major effect on the anion gap, providers may use an albumin correction to estimate a corrected anion gap. This is especially important in hypoalbuminemia, where the unadjusted value may seem artificially low.
The purpose of the adjustment is to compensate for low negatively charged protein levels. In other words, if albumin is reduced, the measured gap may overlook the presence of excess acids. A corrected value can therefore give a better picture of the patient’s real acid-base status.
Several correction methods exist, and the exact approach may change by clinician or institution. The important point is that the adjustment should be used when albumin is abnormal, because it improves the usefulness of the anion gap as a screening tool and promotes more accurate patient evaluation.
Albumin correction does not replace the original result. Instead, it offers context and helps prevent missing a significant acid-base imbalance when albumin is low.
Typical Causes of an Abnormal Anion Gap
An abnormal anion gap may suggest several different conditions, so the result must be connected to the rest of the case. Frequent causes of a high value include:
- Metabolic acidosis with build-up of acid Lactic acidosis Ketoacidosis Renal failure Toxin ingestion
In addition, certain substances can affect the calculation or resemble an abnormal pattern. Some toxic exposures alter the expected balance of measured and unmeasured ions. A detailed review of medications, exposures, and symptoms is part of sound clinical interpretation.
A low value may stem from hypoalbuminemia, lab error, or other testing issues. Since the anion gap is derived from a blood chemistry panel, the quality of the input values directly affects the final result. That makes it a valuable but indirect marker in a broader medical assessment.
Whenever the result is abnormal, clinicians should ask whether the pattern fits the patient’s condition, whether the value is consistent with the lab’s reference range, and whether repeat testing is needed.
How to Interpret Results Safely
The safest way to interpret an anion gap is to look beyond the number itself. The result is part of a bigger picture that includes the patient’s symptoms, other laboratory data, and the suspected cause of any acid-base balance problem. A single value does not mean a diagnosis.
First, confirm the number against the reporting lab’s normal range and reference range. Then assess whether the patient has evidence of metabolic acidosis, kidney dysfunction, infection, diabetes complications, or a possible toxin ingestion. If albumin is low, consider a corrected anion gap before drawing conclusions.
It is equally important to remember that the anion gap is a clinical marker, not a complete explanation. It can point toward a category of problems, but additional testing may be required to identify the exact cause. This may include repeat chemistry tests, blood gas testing, lactate measurement, ketones, kidney function studies, or toxicology evaluation.
In practical terms, consider the anion gap as a systematic part of the medical interpretation of unexpected test findings. Such an approach can reduce missed findings and promotes better care.
Frequently Asked Questions
What is the formula for anion gap?
The usual anion gap formula equals serum sodium less the total of serum chloride and serum bicarbonate. Expressed mathematically, it is: Anion gap = sodium − (chloride + bicarbonate). Numerous anion gap calculator resources follow the exact calculation method.
What is a normal anion gap value?
The typical range varies by the testing facility and its reference range, but many results land in the lower single digits to teen range when reported in mEq/L. Always compare the result with the lab’s own reference standard rather than relying on a universal threshold.
Why would an anion gap be high?
A elevated anion gap typically indicates extra acids or unmeasured anions are present. Frequent causes are lactic acidosis, ketoacidosis, renal failure, and certain kinds of toxin ingestion. It is commonly an indication of metabolic acidosis or another acid-base problem.
Can low anion gap be serious?
Yes, although it is less common. A low anion gap may result from decreased albumin, laboratory error, or additional abnormalities. It may be harmless in some cases, but it can also indicate an issue that deserves further assessment, especially if other blood test results are abnormal.
Is it appropriate to albumin be used to correct the anion gap?
Yes, albumin should be factored in when interpreting the result, especially if albumin is low. Correction for albumin can provide a more accurate adjusted anion gap and help avoid missing a hidden acid-base problem. This is particularly useful in hypoalbuminemia and during broader clinical assessment.